

The way dr practices operate inside hospitals has changed substantially in the last five years. Between workforce shortages, credentialling complexity, and the shift toward hybrid employment models, the systems that used to work have been rewritten. If you're working locum shifts or managing a department that relies on them, understanding how dr practices function now matters more than it did in 2020. This is not about theory. It's about what works when you're rostering a shift in Anaesthetics for tomorrow morning or trying to credential a VMO who trained interstate.
What DR Practices Actually Mean in 2026
When we talk about dr practices, we're referring to the operational frameworks that govern how doctors are engaged, credentialed, rostered, and managed across hospital systems. It includes everything from AHPRA verification to how a locum books a shift in a regional Emergency Department on 48 hours' notice.
The term covers both the administrative scaffolding and the clinical expectations. A hospital's dr practices determine whether a registrar can start work on Monday or needs another week of paperwork. They decide whether a VMO placement in O&G requires five documents or fifteen. They set the tone for how locum work is perceived, whether it's seen as stopgap labour or as a managed, professional model of care delivery.
Most hospitals now operate a mix of permanent staff, visiting medical officers, and locum doctors across all major specialties. The dr practices that support this model need to account for credentialling variability, indemnity insurance requirements, rostering complexity, and the reality that many locums work across multiple states. A doctor who does a Friday in Sydney and a Monday in Brisbane is not unusual anymore. The systems have to accommodate that.
How Credentialling Shapes DR Practices
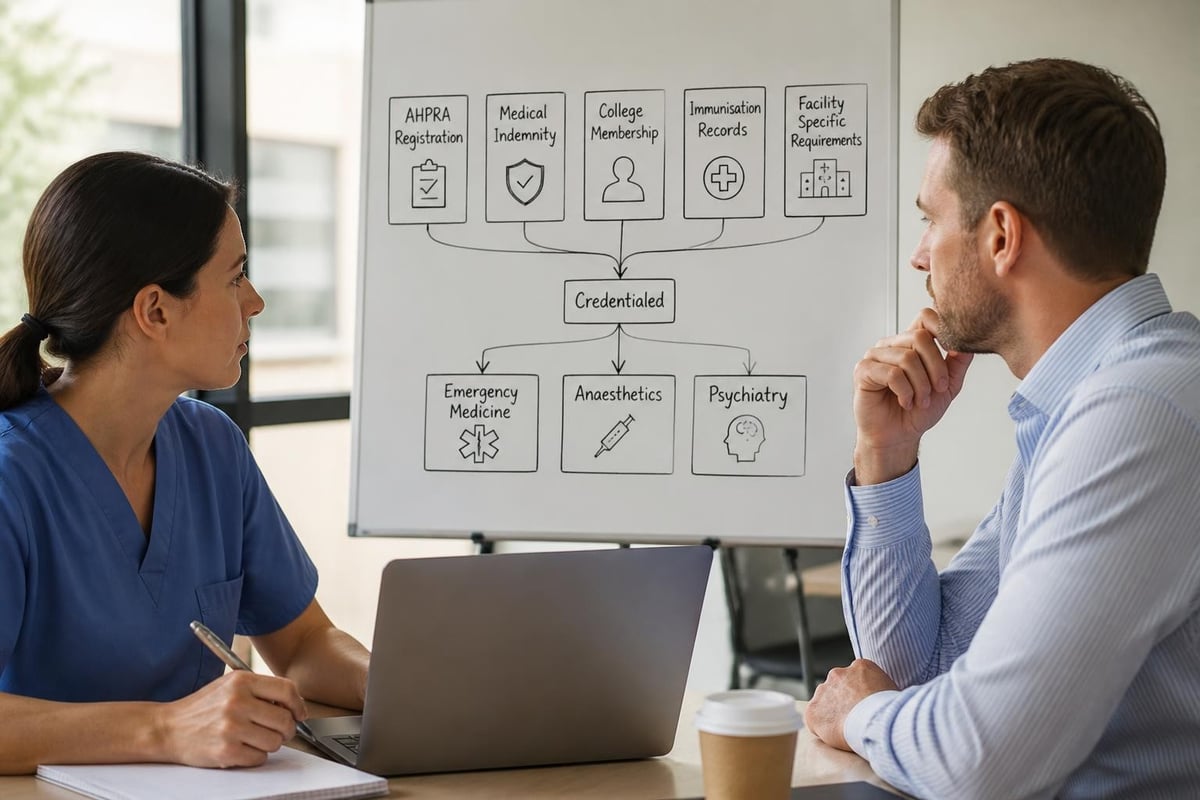
Credentialling is the foundation. Without it, nothing else happens. Every placement starts with AHPRA registration, current medical indemnity insurance, relevant college memberships, and facility-specific checks. The difference between a well-managed process and a chaotic one is how much of this is standardised.
Before any doctor is placed, doctor credentialling and compliance verification should confirm every required document is current and complete. In 2026, that means more than a quick AHPRA lookup. It includes checking state-specific requirements, verifying immunisation records, confirming right-to-work status, and ensuring the doctor's scope of practice matches the role they're being placed into.
The hospitals with the best dr practices treat credentialling as a clinical governance issue, not an HR task. They involve senior medical staff in the review process. They don't credential a doctor for Emergency Medicine and then roster them into ICU without additional checks. They maintain version-controlled records and re-credential annually, not just when someone raises a question.
For locum agencies, the credentialling process is managed in-house by clinicians who understand what they're verifying. A practising doctor reviewing credentials brings a different lens than an administrator working from a checklist. That distinction shows up in placement quality and in how quickly issues are identified before a shift starts.
How Rostering Works Across Hospital Specialties
Rostering is where dr practices either hold up or collapse. A hospital that rosters well can absorb unexpected leave, manage surge demand, and maintain continuity across departments. A hospital that rosters poorly runs the same three doctors into the ground while leaving gaps unfilled.
The difference comes down to planning. Reactive rostering means filling shifts as they become urgent. Planned rostering means identifying gaps weeks in advance and booking doctors before the shortage becomes critical. In Emergency Medicine, Anaesthetics, ICU, O&G, Paediatrics, Psychiatry, and Surgery, planned rostering is the only model that works consistently.
Dr practices in 2026 increasingly involve partial or full roster management by external providers. Rather than a department calling around to fill Friday night's ED shift on Thursday afternoon, the roster is planned a month out with confirmed doctors already credentialed and ready. This is not about outsourcing clinical decision-making. It's about removing the administrative load so department heads can focus on patient care instead of spreadsheets.
Hospitals with preferred supplier arrangements benefit from pre-established relationships with locum providers. The procurement process is already complete. The credentialling standards are already agreed. When a shift needs filling, the conversation is about availability and specialty match, not contracts and compliance documentation.
Matching Doctors to Shifts
Not every doctor suits every shift. Dr practices that work well account for this. A registrar with strong Emergency Medicine experience but limited ICU exposure should not be rostered into a solo ICU shift at a regional hospital without senior backup. A VMO who usually works in a metropolitan teaching hospital may need additional briefing before starting at a smaller facility with different equipment and different patient flow.
Specialty matching is the baseline. Beyond that, there's experience level, facility type, geography, and the doctor's own preferences. A locum who lives in Sydney and regularly works at Royal Prince Alfred has different expectations than a locum who travels interstate for week-long blocks in regional Queensland. Both are valid models. The dr practices need to support both.
The best matches happen when the agency or facility takes time to understand what the doctor is comfortable with and what the shift actually requires. A four-hour ED shift on a Saturday morning in a suburban hospital is not the same as a 24-hour solo cover shift in a rural base hospital. Treating them as interchangeable leads to poor placements and doctors who don't return.
Clinical Governance and DR Practices
Clinical governance in dr practices means accountability for who is placed, where, and under what supervision. It means knowing that the doctor rostered into Anaesthetics tomorrow has current ANZCA credentials, appropriate indemnity cover, and experience in the procedures likely to come up during the shift.
In 2026, this is managed through structured systems. ISO 9001:2015 certification, for example, ensures that processes are documented, repeatable, and independently audited. It means credentialling is not done differently each time depending on who is handling the file. It means the process for verifying a doctor's qualifications in February is the same as the process in September.
For hospital clients, clinical governance also means understanding who is accountable when something goes wrong. If a locum doctor is placed and later found to have incomplete credentials, who identified the gap and what happens next? Dr practices built on strong governance models answer those questions before they're asked.
| Governance Element | What It Covers | Why It Matters |
|---|---|---|
| Credentialling oversight | AHPRA, indemnity, college memberships, immunisations | Prevents unqualified placements |
| Scope-of-practice verification | Matching specialty credentials to rostered shifts | Reduces clinical risk |
| Annual audit process | Independent review of credentialling and placement records | Ensures compliance continuity |
| Incident escalation pathways | Clear reporting lines when issues arise mid-shift | Supports rapid response |
Governance is not bureaucracy for its own sake. It's the framework that lets hospitals trust the doctors they roster and lets doctors trust the facilities they walk into.
Short-Term vs Long-Term Placements
Dr practices differ depending on whether the placement is a single shift or a six-month contract. Short-term placements require fast turnaround. A hospital calls on Tuesday for a shift on Friday. The doctor needs to be credentialled, briefed, and confirmed within 72 hours. That only works if the credentialling is already current and the doctor is familiar with the facility type.
Long-term placements allow more time but require more planning. If a hospital needs cover for parental leave or extended sick leave, the placement might run for three months. The doctor needs accommodation, a clear understanding of the clinical environment, and continuity with the department. The dr practices that support this involve onboarding, regular check-ins, and structured handover when the placement ends.
Both models go through the same credentialling process. Duration does not change the compliance requirements. A two-day placement and a two-month placement both require current AHPRA registration, verified indemnity, and facility-specific checks. The difference is in logistics and relationship management, not in standards.

Interstate and Regional Considerations
Dr practices become more complex when placements cross state lines or move into regional settings. A doctor credentialled in New South Wales may need additional checks to work in Queensland. A VMO used to working in a metropolitan private hospital will face a different clinical environment in a regional base hospital with fewer resources and different patient demographics.
Travel and accommodation logistics matter more in regional placements. A locum flying into a regional town for a week needs confirmed accommodation before departure, clear directions to the facility, and contact details for on-site support. These are not minor details. They affect whether the doctor arrives ready to work or arrives stressed and underprepared.
Dr practices that manage regional placements well involve pre-placement briefings. The doctor knows what equipment is available, what backup exists, and what the typical patient load looks like. If the facility uses a different EMR system, that's flagged in advance. If there's no on-site pathology and samples need to be couriered, the doctor knows before the first shift starts.
Interstate work also brings taxation and payroll complexity. Depending on how the doctor is engaged, they may be invoicing as a contractor or employed directly by the facility. The dr practices need to make this clear from the beginning so the doctor knows how they'll be paid and when. Agencies that handle invoice management and payment follow-up remove that administrative burden entirely.
What Doctors Actually Want from DR Practices
Doctors doing locum work want clarity, speed, and reliability. They want to know what the shift involves before they commit. They want credentialling handled efficiently so they're not chasing paperwork three days before the shift starts. They want to be paid on time without having to follow up invoices themselves.
Dr practices that deliver on these basics attract better doctors and keep them engaged for future placements. Facilities and agencies that make the process difficult or unpredictable lose access to the best locum workforce. In a tight market, that matters.
Doctors also want clinical autonomy appropriate to their level. A registrar expects supervision pathways. A VMO expects to work independently within their scope. Dr practices need to match expectations to reality. Promising a senior role and then micromanaging every decision creates friction. Placing a junior doctor in a role that requires independent complex decision-making creates risk.
How Locum Agencies Fit into DR Practices
Locum agencies are part of the dr practices infrastructure now, not an add-on. Hospitals use agencies because maintaining an internal locum network, managing credentialling, handling rostering, and coordinating logistics is a full-time role that most facilities cannot resource internally.
Agencies with preferred supplier status across state health departments bring pre-approved procurement pathways. A hospital does not need to run a tender process or negotiate a new contract. The agency is already vetted. The hospital can access the doctor network immediately and focus on clinical fit rather than administrative setup.
The best agencies operate as an extension of the hospital's medical workforce team. They understand the facility's needs, they know which doctors have worked there before, and they manage the placement process end-to-end. That includes credentialling, rostering, travel coordination, and payment administration.
For doctors, working with an agency that manages these details means less administrative work and more focus on clinical practice. It also means access to a wider range of placements. An agency with national reach can offer shifts in Sydney one week and Brisbane the next, with all the logistics handled in between.
| Agency Function | What It Delivers | Who Benefits |
|---|---|---|
| Credentialling management | AHPRA, indemnity, college verification before placement | Hospital and doctor |
| Rostering coordination | Planned cover across specialties and facilities | Hospital department heads |
| Travel and accommodation logistics | Flights, accommodation, transport arranged pre-departure | Doctor, especially regional placements |
| Invoice and payment follow-up | Timely payment without doctor involvement | Doctor |
| 24/7 consultant support | Real-time issue resolution during shifts | Doctor and hospital |
Agencies are judged on speed, accuracy, and whether the placements work clinically. Dr practices built around strong agency partnerships operate more smoothly than those trying to manage everything internally with limited resources.

Registrar and VMO Differences in DR Practices
Registrars and VMOs require different approaches within dr practices. Registrars are generally earlier in their training. They expect supervision, teaching opportunities, and structured feedback. VMOs are consultants. They expect clinical autonomy, appropriate facilities, and respect for their expertise.
Rostering a registrar into a metropolitan teaching hospital is straightforward. There's supervision on-site, established teaching rounds, and a structured environment. Rostering a registrar into a regional base hospital requires more planning. Who provides supervision? What happens if a complex case presents? What are the escalation pathways?
VMO placements in specialties like Anaesthetics, Surgery, O&G, Psychiatry, Paediatrics, and ICU require higher credentialling specificity. The facility needs to verify not just general credentials but specific procedural experience. A VMO credentialled for general surgery may not be credentialled for laparoscopic bariatric procedures. The dr practices need to distinguish between general scope and specific competencies.
For both groups, the placement needs to match the clinical environment to the doctor's experience and expectations. A registrar expecting a busy teaching hospital environment will struggle in a quiet rural setting with limited peer interaction. A VMO expecting consultant-level autonomy will struggle in a facility that treats all locums as supervised juniors.
Payment, Invoicing, and Administrative Load
Dr practices that work well remove administrative friction. Doctors should not spend hours chasing invoices or clarifying payment terms after a shift is complete. Agencies that handle invoicing and payment follow-up take that task off the doctor's plate entirely.
For doctors employed directly by the facility, payment terms should be clear from the outset. When is the first pay cycle? How are overtime or after-hours rates calculated? What happens if there's a public holiday during the placement? These are not difficult questions, but they need answers before the shift starts.
For contractors, invoicing needs to be straightforward. The agency submits the invoice, follows up with the facility, and ensures payment within agreed terms. The doctor gets paid without needing to track down accounts payable or send reminder emails. This is basic operational competence, but not every agency delivers it consistently.
In 2026, payment delays are one of the fastest ways to lose access to good locum doctors. Word spreads quickly. A facility or agency known for slow payment or disputed invoices will struggle to fill shifts. Dr practices built around reliable, timely payment attract better doctors and retain them for future placements.
What Works and What Doesn't
Dr practices that work share common features. They plan ahead rather than react. They credential thoroughly and early. They match doctors to shifts based on specialty, experience, and clinical environment. They communicate clearly. They pay on time.
Dr practices that fail tend to collapse in predictable ways. They roster reactively, filling shifts at the last minute. They skip credentialling steps to save time. They place doctors into roles that don't match their scope or experience. They leave logistics to chance. They delay payment or dispute invoices without clear reason.
The gap between functional and dysfunctional dr practices is not about resources. Small regional hospitals with limited budgets can run excellent locum programs if they plan well and work with reliable partners. Large metropolitan hospitals with substantial resources can run chaotic programs if they treat locum work as an afterthought.
For doctors considering locum work, the quality of dr practices is one of the clearest indicators of whether a placement will be professionally satisfying or frustrating. A well-run placement feels seamless. A poorly run placement feels like administrative chaos from start to finish. The difference is visible within the first 24 hours.
Dr practices in 2026 are defined by how well they integrate credentialling, rostering, clinical governance, and logistics into a system that works for both hospitals and doctors. The hospitals and agencies that get this right attract better doctors, maintain continuity of care, and operate more efficiently. If you're working locum shifts or managing a department that relies on them, partnering with an organisation that understands these systems makes the difference between functional and frustrating. Best Practice Medical connects exceptional doctors with extraordinary locum opportunities across Australia, handling credentialling, rostering, and placement logistics so hospitals and doctors can focus on clinical care rather than administrative complexity.