

Health care practitioners are the clinical workforce on which Australia's hospital system depends. The term applies to registered medical professionals including specialists, visiting medical officers, registrars, and junior doctors who diagnose, treat, and manage patients across emergency departments, surgical theatres, intensive care units, obstetric wards, and psychiatric services. In 2026, the demand for health care practitioners across public and private hospitals in New South Wales, Queensland, Victoria, and every other state and territory shows no sign of slowing. Facilities continue to grapple with gaps in rosters, credentialling complexity, and the administrative overhead of ensuring every practitioner on site is appropriately registered, insured, and competent for the clinical environment they are entering.
What defines a health care practitioner in the hospital context
Health care practitioners in Australian hospitals hold current registration with the Australian Health Practitioner Regulation Agency (AHPRA). That registration is specialty-agnostic at the regulatory level, but the work performed is not. A registrar in anaesthetics is credentialled differently than a paediatric hospitalist, and a VMO covering surgical lists has different college requirements than a psychiatry consultant.
The breadth of the term can create ambiguity in staffing conversations. When a hospital says it needs health care practitioners for a weekend block, the question becomes: which specialty, which seniority, and what level of supervision is required? A JMO working in a regional hospital under supervision is classified identically by AHPRA as a senior consultant anaesthetist working independently in a metropolitan private hospital, but the credentialling and placement considerations differ substantially.
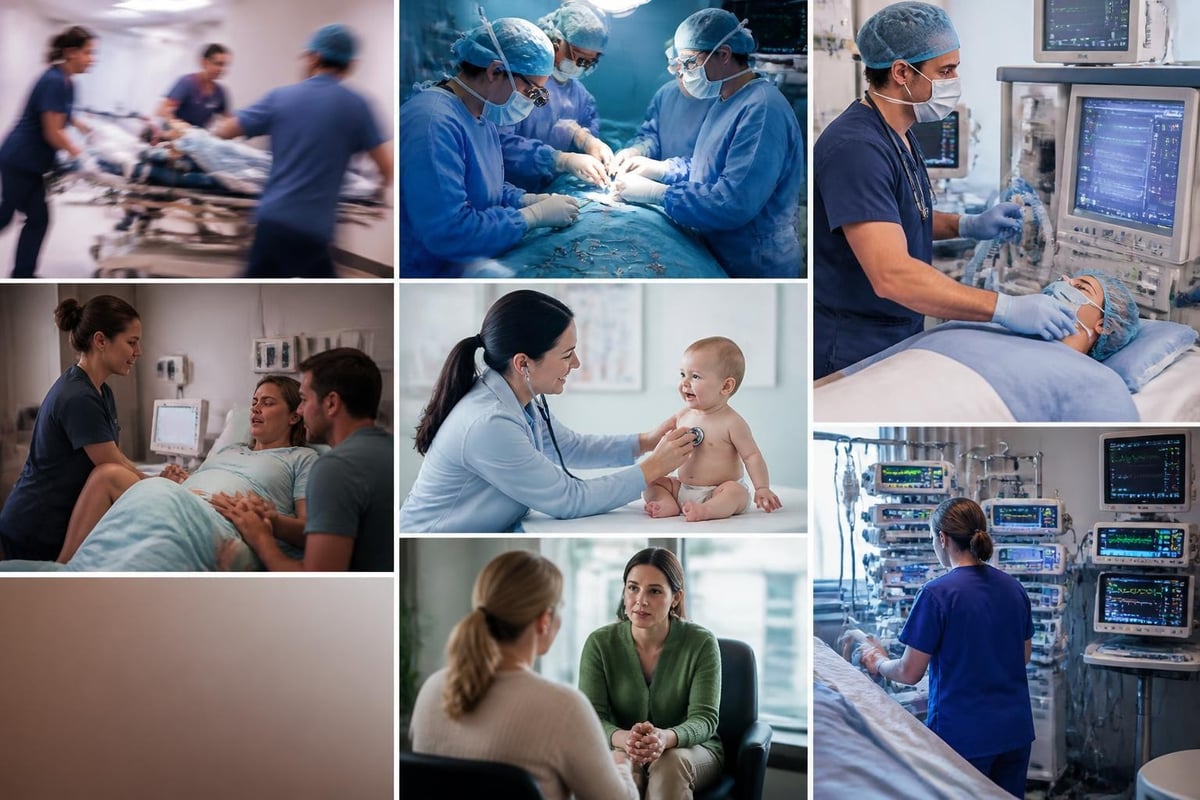
From a placement perspective, health care practitioners are matched based on specialty training, current AHPRA registration status, medical indemnity cover, and whether they hold the relevant college fellowship or are training within a recognised program. Public hospital systems and private hospital groups increasingly require proof of college membership or progression through a specialty training pathway before granting access to rosters, particularly for higher-acuity departments.
Registration and credentialling requirements
Every health care practitioner working in an Australian hospital must hold general or specialist registration with AHPRA. General registration allows supervised practice; specialist registration is granted after completion of an approved training program and fellowship examination. The gap between the two categories matters when filling locum shifts or extended placements, because supervised practitioners cannot work autonomously in most settings.
AHPRA registration alone does not grant hospital access. Facilities layer additional credentialling requirements on top of regulatory registration. These include current medical indemnity insurance, immunisation records, police checks, working with children checks (where relevant), and proof of recency of practice in the proposed specialty. The World Health Organization's health workforce resources provide context for why credentialling exists at multiple levels: patient safety, professional accountability, and workforce quality assurance.
Most facilities also require health care practitioners to complete orientation modules, demonstrate familiarity with the hospital's electronic medical record system, and confirm they understand escalation protocols for clinical emergencies. These are not trivial administrative steps; they are the difference between a practitioner who can start confidently on day one and one who becomes a risk to themselves and the department.
Credentialling standards are independently audited in accredited placement systems. ISO 9001:2015 certification, for example, requires documented verification of every credential before a practitioner is placed, and annual external audits to confirm the process is followed consistently. This removes the risk of assuming a practitioner is appropriately registered or insured when they are not.
The role of health care practitioners across hospital specialties
Health care practitioners do not work uniformly across the hospital. Their clinical responsibilities, supervision requirements, and shift structures vary by specialty and seniority. In Emergency Medicine, a senior registrar might run resuscitations and manage the department overnight with consultant oversight via phone. In Anaesthetics, a VMO covers elective surgical lists independently and is rostered for on-call trauma work.
Emergency Medicine: Health care practitioners in ED triage, stabilise, and manage undifferentiated patients. Senior practitioners assess and discharge, while junior doctors work under supervision. Credentialling for ED requires ACEM training or equivalent, current ACLS and APLS certification, and familiarity with the facility's trauma protocols.
Anaesthetics: Practitioners provide perioperative care, manage airways, and deliver sedation or general anaesthesia. Credentialling is strict. ANZCA fellowship or training progression is mandatory in most facilities, and malpractice insurance limits are higher due to the procedural nature of the work.
Intensive Care: ICU practitioners manage ventilated patients, complex sepsis, post-operative complications, and multi-organ failure. CICM fellowship is the standard for independent practice. Junior practitioners rotate through ICU as part of broader training programs but work under close supervision.
Obstetrics and Gynaecology: Practitioners deliver babies, manage high-risk pregnancies, perform caesarean sections, and cover gynaecological emergencies. RANZCOG fellowship is required for VMO appointments. Registrars work within accredited training rotations.
Paediatrics: Health care practitioners in paediatrics assess and treat neonates, infants, children, and adolescents. RACP paediatric training is the standard pathway. Many facilities distinguish between general paediatrics and subspecialties like neonatology or paediatric emergency, with different credentialling thresholds.
Surgery: Surgical practitioners perform operations, manage peri-operative care, and cover trauma. RACS fellowship in the relevant surgical subspecialty (general surgery, orthopaedics, urology, etc.) is mandatory for independent operating privileges. Unaccredited registrars assist but do not operate unsupervised.
Psychiatry: Practitioners assess and manage acute psychiatric presentations, provide inpatient care, and participate in mental health tribunal processes. RANZCP training or fellowship is required. Credentialling also involves understanding the Mental Health Act in the relevant state.
These distinctions matter because facilities do not hire "a doctor"-they hire a health care practitioner credentialled for a specific clinical role within a specific department. Best Practice Medical's specialty matching reflects this reality by sorting placements based on specialty, seniority, and the clinical environment.
Workforce shortages and placement realities
Australia's health care practitioner workforce is unevenly distributed. Metropolitan teaching hospitals in Sydney, Melbourne, and Brisbane attract more applicants than they have positions. Regional and rural hospitals struggle to fill rosters, particularly in specialties like anaesthetics, psychiatry, and obstetrics. The imbalance is structural, not temporary, and it shapes how facilities manage staffing in 2026.
Public hospital systems in New South Wales, Queensland, Victoria, the Australian Capital Territory, Western Australia, Tasmania, and the Northern Territory rely on locum placements to cover gaps caused by leave, vacant positions, or short-term demand spikes. These placements range from single shifts to multi-month blocks. The credentialling burden for each placement is identical regardless of duration, which is why facilities prefer working with agencies that verify credentials in-house rather than accepting self-reported documentation from practitioners.

The U.S. Department of Health and Human Services' workforce report identifies similar patterns internationally: shortages are concentrated in high-acuity specialties and geographically isolated areas. In Australia, the added complication is that health care practitioners trained in urban centres often lack familiarity with the resource constraints and clinical autonomy expected in regional hospitals. Briefing a practitioner before they start a regional placement is not optional; it is the difference between a successful engagement and a failed one.
For facilities managing complex or ongoing locum requirements, partial or full roster management services allow hospitals to plan ahead rather than fill shifts reactively. Preferred supplier status with state health departments and major private hospital groups supports this administratively, removing procurement friction and allowing health care practitioners to be placed without lengthy onboarding delays.
Short-term vs extended placements
Short-term placements cover single shifts, weekend blocks, or week-long gaps. Extended placements replace a practitioner on parental leave, long service leave, or extended sick leave, and can run for several months. Both require the same credentialling rigour, but the briefing and logistical support differ.
| Placement Type | Duration | Common Use Cases | Credentialling Timeline | Logistical Complexity |
|---|---|---|---|---|
| Short-term | 1 shift to 2 weeks | Annual leave, sick leave, sudden resignation | 3-5 business days | Low (accommodation rarely needed) |
| Extended | 4 weeks to 6 months | Parental leave, prolonged illness, recruitment gap | 7-14 business days | High (relocation, accommodation, orientation) |
| Ad hoc on-call | Variable | On-call rosters, surge capacity | Already credentialled | Moderate (practitioner must be locally available) |
Health care practitioners working extended placements in unfamiliar locations benefit from pre-arranged accommodation and travel coordination. For interstate or regional placements, having flights, accommodation, and ground transport confirmed before departure removes uncertainty and allows the practitioner to focus on preparation rather than logistics.
Telehealth and evolving practice models
Telehealth expanded rapidly during the pandemic and has remained a component of Australian hospital practice in 2026, particularly for rural outreach, post-discharge follow-up, and specialist consultations. Health care practitioners delivering telehealth services are subject to the same AHPRA registration requirements as those providing in-person care, and facilities are increasingly asking for evidence of telehealth experience during credentialling.
Medicare telehealth policy in the United States outlines the billing and compliance landscape for remote consultations, and while Australian arrangements differ, the underlying principle is consistent: telehealth is clinical work, not an administrative workaround, and it requires appropriate training and documentation.
For health care practitioners working locum shifts, telehealth can mean being asked to participate in virtual ward rounds, provide specialist input to a regional hospital via video link, or deliver follow-up consultations to discharged patients. These are not universally expected, but they are increasingly common, and practitioners who are comfortable with the technology and clinical workflow have more placement options.
Patient safety and practitioner accountability
Patient safety is the non-negotiable standard in every placement. Health care practitioners entering a new facility must understand the escalation pathways, the electronic medical record system, the layout of resuscitation equipment, and the on-call structure for each specialty. These are not things that can be assumed or learned on the fly.
The AHRQ Patient Safety Network provides case studies and toolkits that highlight how miscommunication, unfamiliarity with systems, and gaps in orientation contribute to adverse events. For locum health care practitioners, the risk is higher because they are working in an unfamiliar environment without the institutional knowledge that permanent staff accumulate over time.
Facilities mitigate this risk through structured orientation, clear documentation of clinical protocols, and 24/7 access to senior support. Agencies that place health care practitioners mitigate it by briefing practitioners before they start, verifying that credentials are current, and maintaining contact throughout the placement to resolve issues as they arise.
Practitioners who understand the benefits of locum work know that patient safety is also self-protection. Working in a facility where you do not understand the protocols or cannot access timely support exposes you to clinical risk and professional liability. A credible placement service ensures those gaps do not exist.
Compensation, taxation, and administrative burden
Health care practitioners working locum shifts are typically engaged as contractors rather than salaried employees. This means they invoice for hours worked, manage their own taxation, and are responsible for superannuation contributions. Rates vary by specialty, seniority, location, and shift type. A weekend ED shift in a regional hospital pays more than a weekday surgical assist in a metropolitan private facility.
Contractors must hold their own medical indemnity insurance, maintain an ABN, and submit invoices correctly to ensure timely payment. For time-poor practitioners, the administrative burden of chasing unpaid invoices or reconciling payslips with actual hours worked is a genuine frustration. Invoice management and payment follow-up services remove this burden by handling the submission, tracking, and escalation of outstanding amounts on the practitioner's behalf.
For practitioners employed directly by a facility for an extended placement, the facility manages payroll, superannuation, and tax withholding. In these cases, the role of a placement agency is to ensure payment terms are clear from the outset and that there are no discrepancies when the first pay cycle arrives.
Tax and superannuation considerations
Contractors are responsible for quarterly Business Activity Statements (BAS), end-of-year tax returns, and superannuation contributions. Many health care practitioners engage an accountant to manage this, but the obligation remains theirs. Practitioners new to contracting sometimes underestimate the tax liability and are surprised when June arrives.
Superannuation for contractors is not automatic. You must set up a self-managed super fund or nominate a fund and make contributions yourself. This is different from salaried employment, where the employer contributes on your behalf. Practitioners who alternate between salaried and contract work need to track contributions across both arrangements to avoid shortfalls.
Credentialling oversight and clinical governance
Credentialling is not a set-and-forget process. Health care practitioners must renew AHPRA registration annually, maintain continuous medical indemnity cover, and update immunisation records as required. Facilities expect these documents to be current at the time of engagement, not "in progress" or "pending renewal."
Agencies that place health care practitioners in hospitals manage credentialling verification in-house. This means checking AHPRA registration directly via the public register, confirming insurance policy dates and coverage limits, and verifying college membership through official channels. Self-reported documentation is not sufficient.
Clinical governance also requires that a practitioner's scope of practice matches the placement. A registrar in an advanced training year can perform certain procedures independently; a junior registrar cannot. A VMO with 20 years of experience in one specialty cannot be credentialled for a different specialty without retraining. These distinctions are obvious to clinicians but are sometimes overlooked in administrative staffing decisions.
For facilities seeking to hire casual staff or manage fluctuating demand, working with a credentialling-focused agency reduces the risk of placing an inappropriately qualified practitioner and the liability that follows.
The future of health care practitioner workforce planning
Workforce planning in 2026 involves more than filling today's gaps. It requires anticipating future demand, understanding training pipeline capacity, and recognising that the supply of health care practitioners in high-need specialties will not keep pace with demand for at least another decade.
Medical colleges continue to cap training positions, and the path from medical school to fellowship in most specialties takes a minimum of 10 years. Immigration pathways for overseas-trained specialists have tightened, and recognition of overseas qualifications remains slow. This means facilities cannot assume that recruitment pressures will ease.
For hospital administrators, this creates a structural dependence on locum health care practitioners to maintain service delivery. For practitioners, it creates opportunity-those willing to work regionally, take on short-notice placements, or cover less popular specialties are in consistently high demand.
The challenge is ensuring that the administrative and credentialling infrastructure keeps pace. Facilities that streamline onboarding, maintain updated practitioner databases, and work with preferred suppliers already approved through government procurement panels can fill gaps faster and with less friction than those starting from scratch each time a need arises.
Health care practitioners are the clinical foundation of Australia's hospital system, and the credentialling, placement, and administrative systems that support them determine whether facilities can maintain safe, effective service delivery. In 2026, the demand for appropriately credentialled specialists, registrars, and junior doctors continues to outpace supply, particularly in regional areas and high-acuity specialties. Best Practice Medical connects health care practitioners with locum opportunities across every major specialty and hospital type in Australia, managing credentialling verification, placement logistics, and ongoing support so both practitioners and facilities can focus on clinical care rather than administrative coordination.